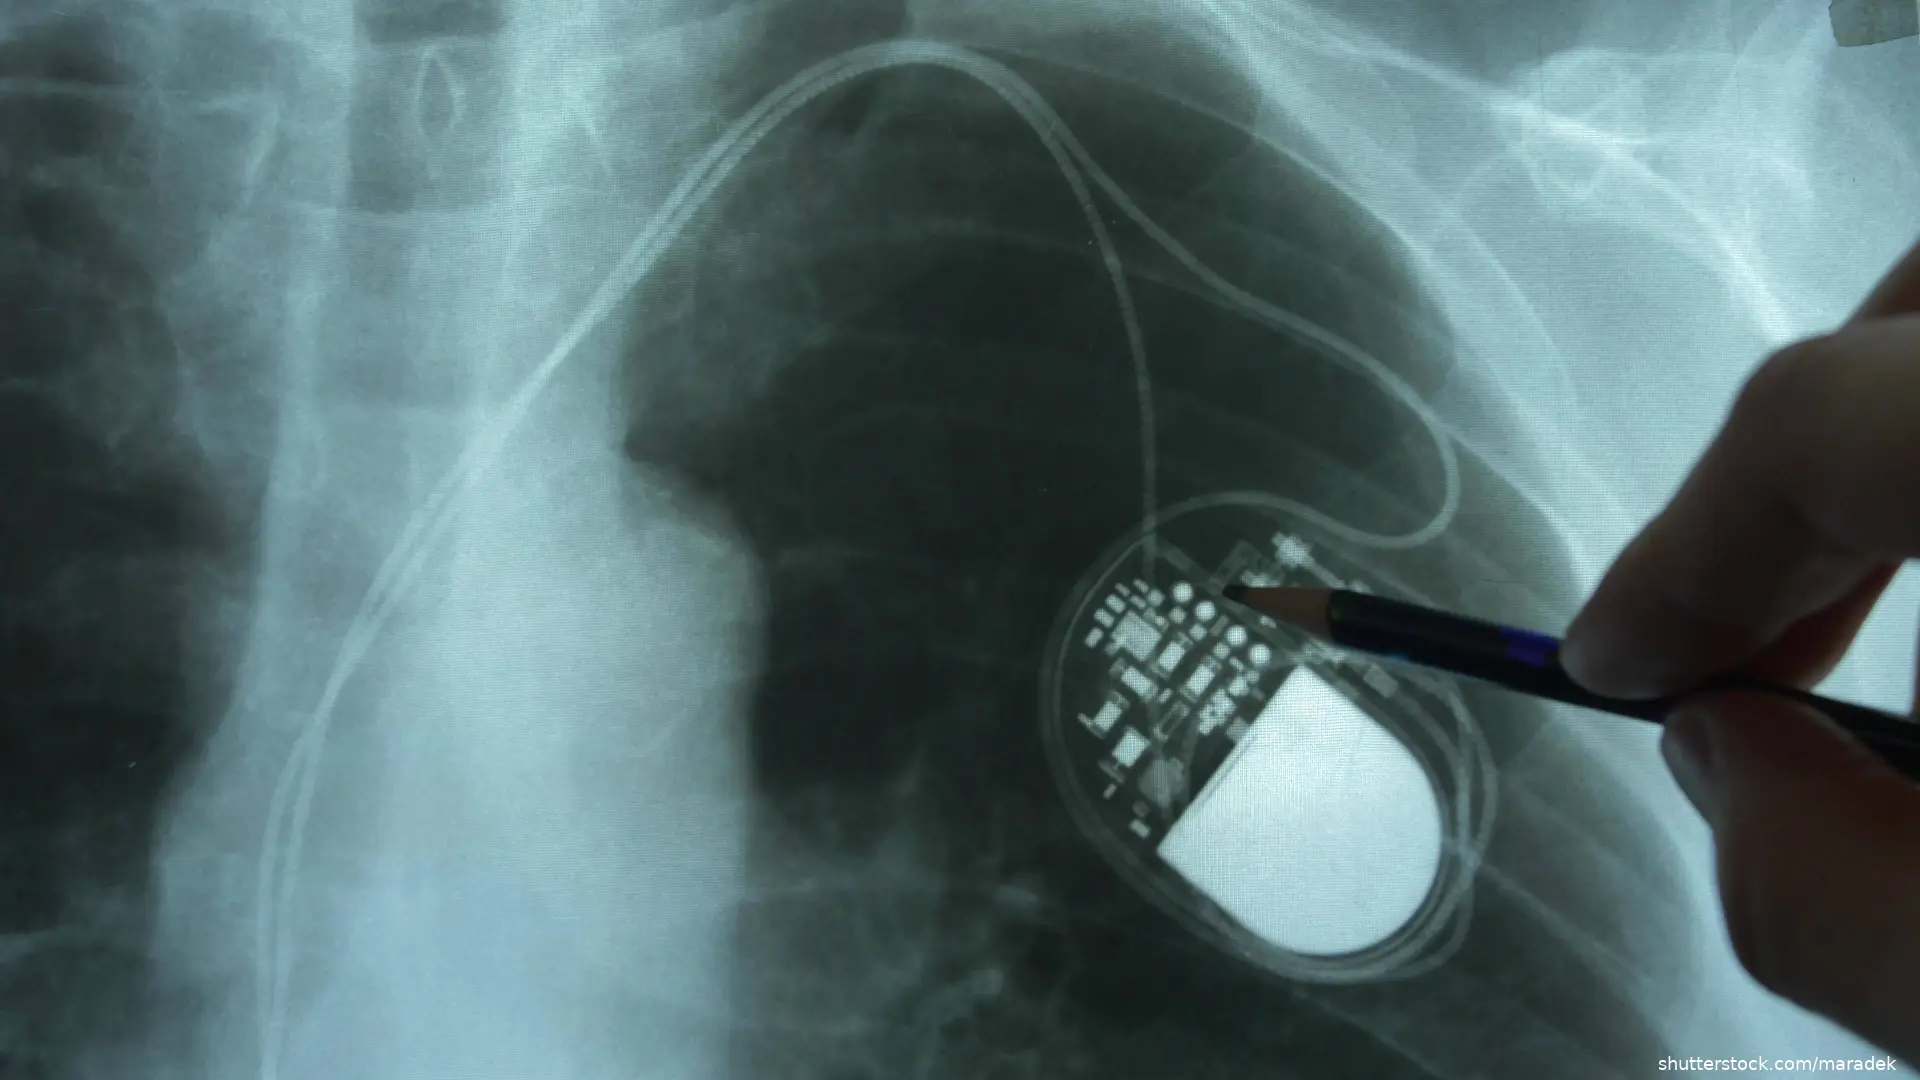
Left bundle-branch area pacing (LBBAP) reduced a 24-month composite of all-cause death, heart failure (HF) events, or upgrade to biventricular pacing compared with right ventricular pacing (RVP) in patients with atrioventricular (AV) block and preserved left ventricular ejection fraction (LVEF), according to results of the LEAP-Block randomized clinical trial published in JAMA.
According to the investigators, the optimal pacing strategy to reduce HF and all-cause mortality remains uncertain for patients with AV block who require high-burden ventricular pacing, and robust comparative evidence on LBBAP vs RVP in this population has been needed.
The prospective, multicenter, superiority trial was conducted at 14 hospitals in China. Of 551 patients with an LVEF of 50% or greater who required ventricular pacing and were assessed for eligibility, 499 with anticipated ventricular pacing greater than 40% were randomly assigned 1:1 to LBBAP or RVP. The primary analysis included 482 patients (mean age, 67 years; 46% female). The primary end point occurred in 2.4% of the LBBAP group and 12.5% of the RVP group (absolute risk difference, −10.1%; 95% CI, −16.8% to −3.4%).
Acute procedural success was comparable between groups (97.9% with LBBAP and 99.6% with RVP), with left bundle-branch capture confirmed in 188 of 236 patients (79.7%). Among secondary outcomes, HF events occurred in 3.4% of the LBBAP group and 11.3% of the RVP group. The investigators observed no significant differences between groups in all-cause death, upgrade to biventricular pacing, device-related complications, or pacing-induced cardiomyopathy. The 24-month Kaplan-Meier estimated cumulative incidence of the primary end point was 5.0% with LBBAP and 13.2% with RVP, and the investigators reported that LBBAP superiority was consistent across all prespecified subgroups.
The investigators concluded that among patients with AV block and preserved LVEF requiring high-burden ventricular pacing, LBBAP was superior to RVP in reducing the risk of the composite end point at 24 months. The trial enrolled patients only at hospitals in China, and the composite components of all-cause death and biventricular pacing upgrade did not differ significantly between groups on their own.
Source: Li X, Wang H, Zhang W, et al. Left bundle-branch area pacing vs right ventricular pacing for atrioventricular block and preserved left ventricular function: the LEAP-Block randomized clinical trial. JAMA. Published online October 28, 2026. doi:10.1001/jama.2026.18146
Advertisement
Today's Joke
Cartoon Slide Show


Quiz

Medical Trivia 10/30/2026
1 questions · ≈ 1 min
to compete in the ranking.
×
Loading