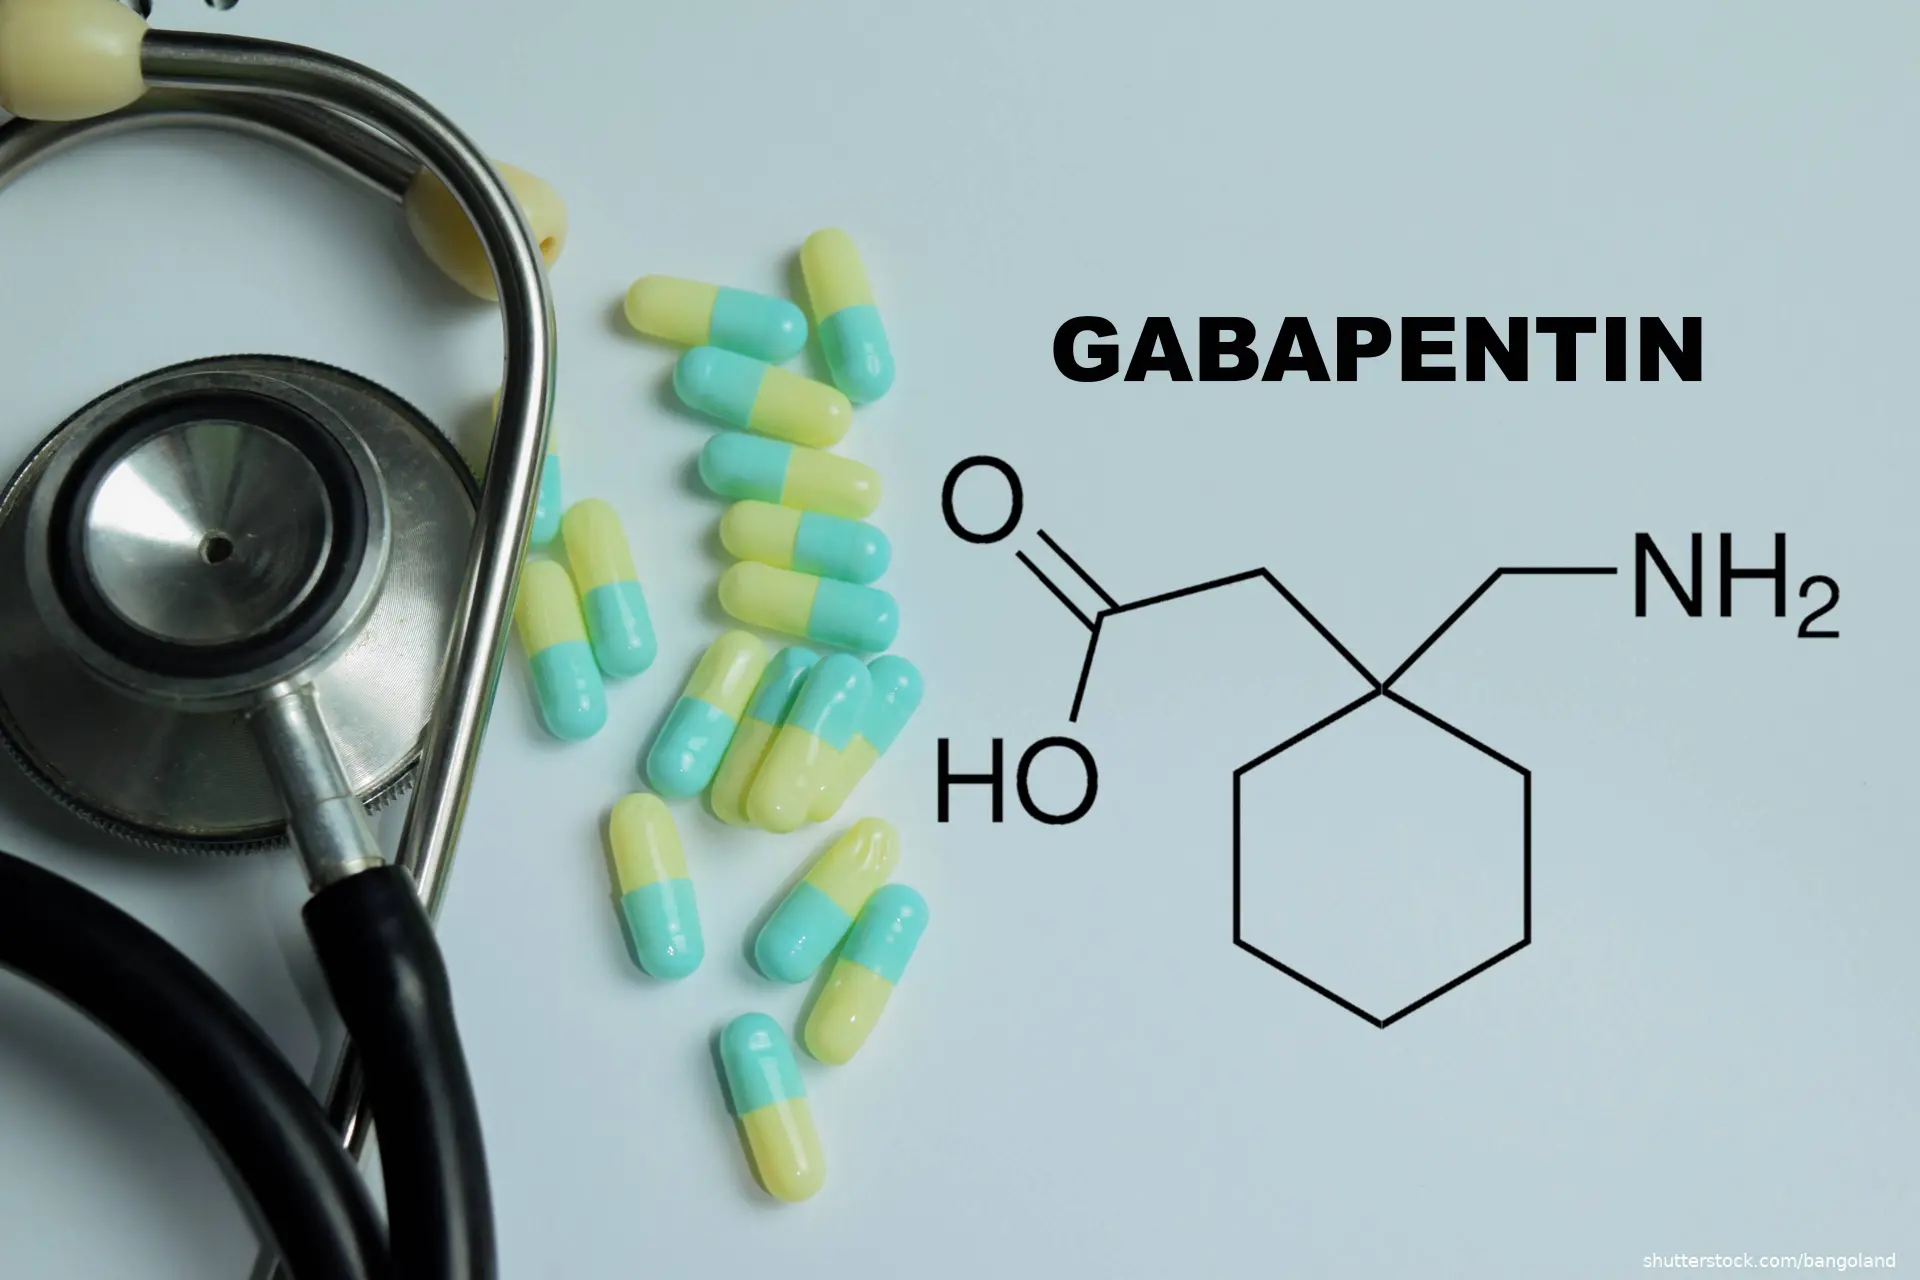
Michigan's 2024 decision to remove gabapentin from its state controlled-substance schedule was associated with an immediate increase in gabapentin dispensing among Medicaid enrollees, according to a research letter published in JAMA Network Open.
Gabapentin is not a federally scheduled controlled substance, though the related gabapentinoid pregabalin has been scheduled under the Controlled Substance Act since its approval. Eight states classified gabapentin as a schedule V controlled substance between 2016 and 2024 to regulate prescribing and reduce misuse-related harms, amid documented risks including respiratory depression and death when combined with opioids and other psychotropic medications. Michigan became the fourth state to schedule gabapentin, in January 2019, then removed that classification in May 2024, a change state regulators attributed partly to aligning with neighboring states and federal policy.
Using a controlled interrupted time-series design, investigators analyzed quarterly Medicaid State Drug Utilization Data on gabapentin dispensing in Michigan from the first quarter of 2023 through the third quarter of 2025, using pregabalin dispensing as a negative control. Gabapentin dispensing ranged from 33 to 43 prescriptions per 1000 Medicaid enrollees over the study period. Descheduling was associated with an immediate increase of 4.00 gabapentin prescriptions per 1000 enrollees relative to pregabalin (95% CI, 2.33-5.67), though no significant change in dispensing trend was observed (0.49 prescriptions per 1000 enrollees per quarter; 95% CI, -0.15 to 1.13).
The study authors noted this cross-sectional, observational design cannot establish causation, since other concurrent interventions may have influenced prescribing. They also cited reliance on dispensing rather than actual medication-use data and a relatively short post-policy observation period as limitations. The authors concluded that scheduling status may influence prescriber behavior and suggested future research examine how controlled-substance classification affects both prescribing and access for patients with legitimate need.
Source: Gora Combs K, Lo-Ciganic W, Yang J, Hincapie-Castillo JM. Gabapentin use in Medicaid after descheduling. JAMA Netw Open. 2026;9(9):e2635059. doi:10.1001/jamanetworkopen.2026.35059

Peter is a physician with experience in clinical research and evidence-based medical content, specializing in translating complex clinical research and emerging medical evidence into accurate, accessible, and clinically relevant information for HCPs.
Advertisement
Today's Joke
Cartoon Slide Show


Quiz
Medical Trivia 9/9/2026
1 questions · ≈ 1 min · 12 players
to compete in the ranking.
×
Loading